venerdì 30 settembre 2005

Periventricular leukomalacia


Findings

Figure 1 (26-day-old neonate). An arrow points to cysts within the brain parenchyma anterior to the right frontal horn. An even larger area of cysts is seen anterior and lateral to the left frontal horn. The cysts are consistent with a diagnosis of cystic periventricular leukomalacia. The ventricles are normal in size. There is no evidence of intraventricular hemorrhage.
Figure 2 (4-day-old neonate). The brain appears normal. Choroid plexus is seen in each normal-sized lateral ventricle. The anterior watershed area cysts seen 22 days later (Figure 1) are not seen. Ventricles do not parallel each other, but rather extend toward each other suggesting that lines drawn through them would meet if extended anteriorly. This fact goes against the diagnosis of agenesis of the corpus callosum.
Figure 3(26-day-old neonate). Cysts are noted within the brain parenchyma in the right peritrigonal area. No ventriculomegaly is seen.
Figure 4 (4-day-old neonate). Some bright echogenicity is seen anteriorly in an area just lateral to the frontal horn of the right lateral ventricle. A larger area of bright echogenicity is seen in the right ventricle's peritrigonal region. Whether this is normal echogenicity that may be caused by the anisotropic effect as the sound beam crosses normal white matter fibers in the region at 90 degrees or this is very subtle echogenic PVL, could not be determined at the time of the US examination.


Diagnosis: Periventricular leukomalacia


Perhaps the most significant pathologic injury that can occur to the premature brain during neonatal life is periventricular leukomalacia (PVL). It is an ischemic abnormality thought responsible for the later development of spastic diplegia and intellectual deficits including learning disorders. It is a major cause of cerebral palsy in children. It is due to necrosis of cerebral white matter at arterial borders (watershed areas). Optic radiations at the ventricular trigone and cerebral white matter just lateral to the frontal horns are the most commonly affected areas noted on US. It was only first described on CT in 1978 and US in 1983. PVL has been well-documented in association with obvious perinatal problems, but has also been noted in newborns without them.

PVL may be difficult to diagnose during its acute phase when affected areas are echogenic, but may appear similar to the normal echogenic periventricular white matter seen surrounding the lateral ventricles, particularly on coronal views. Asymmetry, when comparing right to left sides may be the only hint something is amiss. The echogenic peritrigonal area seen in normal neonates is thought to be due to the anisotropic effect of the US beam passing from its entry at the anterior fontanelle to the white matter fibers in the peritrigonal area at a 90 degree angle.

Although the echogenic phase of PVL may be difficult to separate on US imaging from areas of normal brain, the diagnosis becomes quite easy within 2-3 weeks, when the cystic phase of PVL develops. The cysts are far more readily seen and are quite distinguishable from normal solid brain parenchyma, as noted in our test images. The best areas to note this on US are on either side of the brain, anterior and lateral to the frontal horns (an anterior watershed area) and posterior to the lateral ventricles in the peritrigonal area (a posterior watershed area).

These cystic areas eventually are filled in by gliosis. When this occurs, US will no longer show the abnormality. This suggests that timing is of the essence in making the diagnosis. Some pediatric radiologists recommend head US exams to be performed on at risk premature infants who are asymptomatic at least 2-3 times during their neonatal course. An exam in the first week (day 4-7) is to be performed to analyze for IVH, one at 2-3 weeks for posthemorrhagic hydrocephalus or cystic PVL, and one at 12 weeks if head growth chart readings are of concern and there is, therefore, further concern to diagnose late hydrocephalus.

lunedì 26 settembre 2005

Neurosarcoidosis


Findings

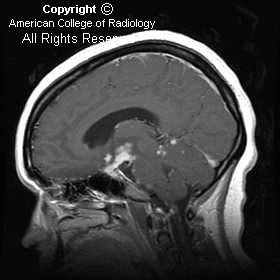
There is a suprasellar mass lesion identified, which is soft-tissue signal on the T2-weighed sequence (Figure 1)
The mass enhances (Figure 2 and 3) along with nodular enhancement in the Sylvian fissures bilaterally (Figure 2), the prepontine region (Figure 3), and the superior vermian region (Figure 3). The pituitary stalk demonstrates dense thick enhancement (Figure 3).


Diagnosis: Neurosarcoidosis


Sarcoidosis is inflammatory disease of unknown etiology, which affects multiple organ systems including the central nervous system. Females are affected more than males and this disease has a 10:1, black to white predominance. Central nervous system involvement occurs in 15% of patients, while symptomatic neurologic involvement is seen in approximately 5%. Dysfunction of cranial nerves and diabetes insipidus are common neurologic presentations. The MR appearance in these patients includes thickening and enhancement of the meningeal surfaces, solitary masses or multiple small, scattered meningeal or parenchymal lesions. When MR imaging shows thickening and enhancement of the pituitary stalk and associated leptomeningeal disease as in this case, sarcoidosis is a very strong possibility, along with meningitis, particularly fungal. Relative T2 hypointensity can be seen commonly, although this can also be seen in cases of fungal diseases, lymphoma, and meningioma.

The diagnosis can be established by performing a Kveim-Siltzbach skin test or by identifying other organ involvement with the intent to biopsy.

lunedì 19 settembre 2005

Spinal intradural extramedullary neurenteric cyst


Findings

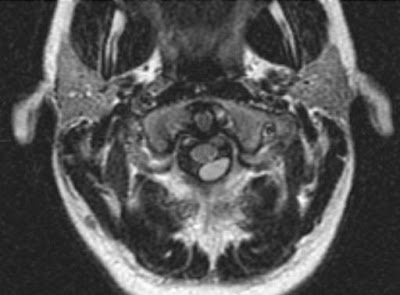
Axial FLAIR MRI sequence demonstrates a well-defined intradural extramedullary lesion posterior to the upper cervical spinal cord (Figure 1).
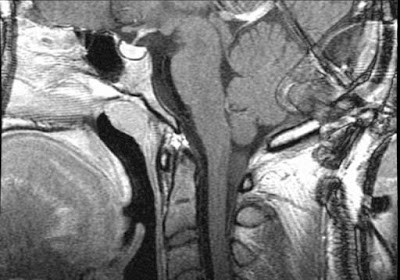
Axial T1 and T2 images show that the lesion is similar, but not identical, to cerebral spinal fluid signal (Figure 2 and Figure 3)
Axial and sagittal T1 post-contrast images demonstrate no associated post-contrast enhancement (Figure 4 and Figure 5).


Diagnosis: Spinal intradural extramedullary neurenteric cyst


Neurenteric cysts of the spine are rare benign cysts that are lined by cells of endodermal origin. They are usually located in the intradural extramedullary space in the cervical and thoracic regions; however, they can be present in the intracranial, intramedullary, and extradural spaces.
Neurenteric cysts can be associated with vertebral body anomalies, tethered cord, diastematomyelia, and spina bifida, and may be connected to mediastinal/abdominal cysts.
Lhermitte's sign refers to a shock-like sensation that extends down the spine and into the extremities with flexion of the neck, which can be caused by any abnormality that causes impingement of the cervical spinal cord (epidural or intradural pathology), spondylosis, multiple sclerosis, spinal cord tumor, radiation myelitis, or vitamin B12 deficiency. In this case, it was the mass effect produced by the neurenteric cyst on the cervical spinal cord, which was resected and pathologically proven.

mercoledì 7 settembre 2005

Choroid plexus papilloma


Findings

Figure 1: CT. Axial cut through level of lateral ventricles. Hyperdense lobulated well-circumscribed mass is noted within the atrium of the right lateral ventricle. There is adjacent compressive edema of the parenchyma of the right parietal lobe, without definitive extension of the mass into the parenchyma. There is moderate hydrocephalus involving both lateral ventricles.
Figure 2: CT. Axial cut through level of frontal horns. Hyperdense mass associated with the right lateral ventricle with adjacent compressive edema on the parenchyma of the right parietal lobe and without definitive extension into the parenchyma is noted. The lateral and third ventricles are moderately dilated. Other images showed the fourth ventricle to be dilated.


Diagnosis: Choroid plexus papilloma


Choroid plexus papillomas are rare tumors arising from the epithelium of the choroid plexus. The choroid plexus produces cerebrospinal fluid. The CSF produced by such a tumor is the key cause of the unusual cases of hydrocephalus due to overproduction of CSF. The overproduction is seen as dilatation of all ventricles in this cause of communicating hydrocephalus. Choroid plexus papillomas represent 60%-70% of tumors of the choroids, 5% of all supratentorial tumors in children, and less than 1% of all primary intracranial tumors. They are usually seen in the first 5 years of life, more typically in infants with signs of significant hydrocephalus. They are much more commonly noted in males.

Classically, they are lobulated isodense to hyperdense masses with occasional punctuate calcifications seen within them. They enhance homogeneously. They usually are seen as an intraventricular mass without extension into or through the ventricular wall. Only aggressive papillomas, accounting for about 5% of cases, will invade adjacent brain.

Although the fourth ventricle is the most common site to find choroid plexus tumors in adults, in children they are usually noted in the lateral ventricle, left more often than right. The ventricular trigone is the most common area of occurrence within the ventricle. The appearance of papillomas in unusual sites has been reported in cases of von Hippel-Lindau syndrome.

Choroid plexus tumors may also be carcinomas, and are usually seen in somewhat older children, aged 3-5 years. Unlike patients with papillomas, those with carcinomas may have focal neurologic signs and signs of hydrocephalus. Involvement is equal for both genders. These tumors most always grow through the ventricular wall.

venerdì 2 settembre 2005

Basilar thrombosis


Diagnosis: Basilar thrombosis


Basilar artery occlusion is found in 1 of every 160 autopsies. Thrombosis of an underlying atherosclerotic, high-grade basilar stenosis is encountered in most of these cases. Embolic occlusion, dissecting aneurysm, trauma, and arteritis are less frequent causes. The site of occlusion is most commonly encountered in the lower third of the basilar artery. Clinically, many patients have a history of hypertension, diabetes mellitus, and previous stroke. The neurological signs and symptoms of basilar artery occlusion vary and may include coma, locked-in syndrome, ocular bobbing, palatal myoclonus, and the crossed paralysis syndromes (eg, Millard-Gubler syndrome of facial palsy and contralateral hemiparesis).

The treatment window of opportunity that resolves or improves the neurological effects of basilar artery occlusion appears to be longer than that for occlusions of the anterior circulation. This might be explained at least in part by the retrograde blood supply to the basilar via the posterior communicating arteries. However, recruitment of pial collaterals during the chronic development phase of the basilar artery stenosis prior to thrombosis likely contributes to this ischemia-resistant phenomenon. Examples have been reported of basilar revascularization and subsequent improvement or normalization of neurologic function following endosurgical recannulization even after 48 hours of occlusion.

Recent management strategies involving both IV and IA thrombolytics have shown significantly improved clinical outcomes compared to previous, mostly supportive regimens. IV thrombolysis using tissue plasminogen activator (tPA) effectively reduces the mortality of basilar thrombosis by more than half (40% from 90%) with recannulization occurring in 52% of cases. IA thrombolysis offers advantages over IV intervention in that lower dosages of pharmacologic agents and mechanical thrombolysis can be used together to macerate, dissolve, and if necessary, physically remove the clot by use of microsnares, balloons, stents, and other devices. Endosurgical treatment has a greater recannulization rate of 80%, a noteworthy statistic when considering that these patients often have higher risk than IV thrombolysis candidates owing to their referral beyond the time window for IV therapy.

lunedì 29 agosto 2005

Grade III IVH


Findings

Coronal plane through frontal horns. Echogenic structures are seen on both sides, just posterior to the frontal horns. An arrowhead points to the echogenic material on the left which may either be in the subependymal area or within the ventricle. Orthogonal parasagittal or transcranial axial views may help differentiate between these possibilities. An arrow points to echogenic material, probably a clot in the temporal tip.
Coronal plane through lateral ventricles. A more posteriorly angulated view than Fig 1 shows the right and left lateral ventricles filled with heterogeneous material. This material consists both of homogeneously echogenic choroid and echopenic, and therefore subacute, clot. Acute clot is homogeneously echogenic similar to normal choroid plexus. Choroid plexus, however, is not seen anteriorly in the frontal horns, ie, anterior to the foramen of Munro.
Parasagittal plane through right lateral ventricle. The orthogonal view helps prove the clot is within a dilated lateral ventricle consistent with a Grade III hemorrhage. An arrowhead points to homogenous echogenic choroids inferior to the clot and not seen extending anterior to the foramen of Munro area, which can be estimated at about midthalamus. In addition, color Doppler can show vascular flow in normal choroid plexus but not in clot.


Diagnosis: Grade III IVH


Premature neonates, particularly those less than 1500 grams or less than 32 weeks gestational age, are at risk for subependymal and intraventricular hemorrhage. Essentially all these hemorrhages develop from bleeding from single-cell thick vessels in the subependymal area of the brain found between the head of the caudate nucleus and thalamus.

A number of years ago, Papille et al created a grading system for hemorrhages that has its proponents and detractors. It however remains an adequate method of communicating areas involved by intracranial subependymal hemorrhage.

Grade I hemorrhage consists of hemorrhage within the subependymal area. Older or resolved Grade I hemorrhages may be imaged as cysts in the subependymal area. This is not the only reason for the development of subependymal cysts.
Grade II hemorrhages extend from the subependymal area into the lateral ventricle with little, if any, ventricular dilatation.
Grade III hemorrhage is intraventricular hemorrhage with dilatation of the involved lateral ventricle.
Grade IV hemorrhages were once thought of as extensions of Grade III hemorrhages into the surrounding brain parenchyma.

In the late 1980s Volpe, noting a difference in timing for the development of echogenic, cystic, or mixed echogenicity areas in the brain compared to the earlier presence by 1-2 days of clot in the ventricle suggested that the intraparenchymal portion of the Grade IV IVH was due to associated venous infarction.
Patients with Grade I and II hemorrhages usually do well clinically. The results for more severe Grade III and IV hemorrhages is less good.

venerdì 19 agosto 2005

Giant parietal foramina


Findings

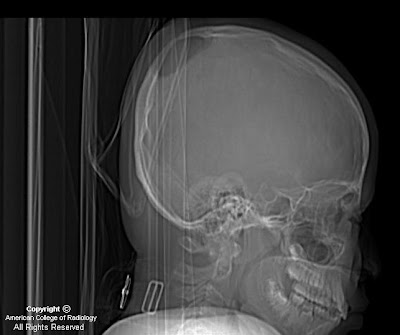
Scout view (lateral view) from a CT scan reveals a large, well-defined parietal calvarial defect.
Brain and bone windows demonstrate bilateral parietal large and symmetric rounded calvarial defects (Figures 2 and 3).
3D surface-shaded reconstructed CT shows to better advantage the 3D characteristics of the calvarial defects and also reveals sagittal and coronal suture synostosis.


Diagnosis: Giant parietal foramina


Giant parietal foramina (GPF) are also known as foramina parietalia permagna, fenestrae parietals symmetricae, enlarged parietal foramina, Catlin marks, and cranium bifidum. GPF is associated with cerebral venous and cortical anomalies, gentic syndromes, and gene mutations. GPS can be an isolated entity, or be inherited in an autosomal dominant fashion. Gene mutations have been linked to both GPS and craniosynostosis. The calvarial defects can be repaired by bone grafts and mesh plating systems in patients at risk for injury to protect the underlying brain from trauma.

There is essentially no differential diagnosis for giant parietal formaina if a good clinical history is obtained (no prior craniectomy, trauma, soft tissue mass associated with the defects, etc). This case illustrates the importance of recognizing the entity of giant parietal foramina. The radiologist should be aware of possible associated intracranial abnormalities such as cortical/cerebral venous anomalies that would be amenable to MRI, MRV, or CTV workup; 3D CT can be very helpful if there is any contemplation of surgical repair.